Stem Cell Therapy for Multiple Sclerosis and Lupus: The 2025-2026 Evidence
PWritten by: Phil KimMedically reviewed by: Dr. Robert Aki, DPMLast medically reviewed: October 8, 2026
When people hear stem cell therapy, many picture an injection into a knee or shoulder. The strongest clinical evidence in all of cell therapy, however, is for a very different procedure: a full stem cell transplant, called autologous hematopoietic stem cell transplantation (AHSCT), used to reset an overactive immune system in diseases like multiple sclerosis and lupus. This article reviews the 2025-2026 evidence and separates the established use from the experimental one.
Jan 2025
when ECTRIMS and EBMT jointly endorsed AHSCT as an option for selected MS patients
BEAT-MS
the NIH-sponsored trial comparing AHSCT against best available drug therapy for treatment-resistant relapsing MS
3
randomized trials showing a survival benefit for transplant over standard chemotherapy in systemic sclerosis
A transplant is not an injection
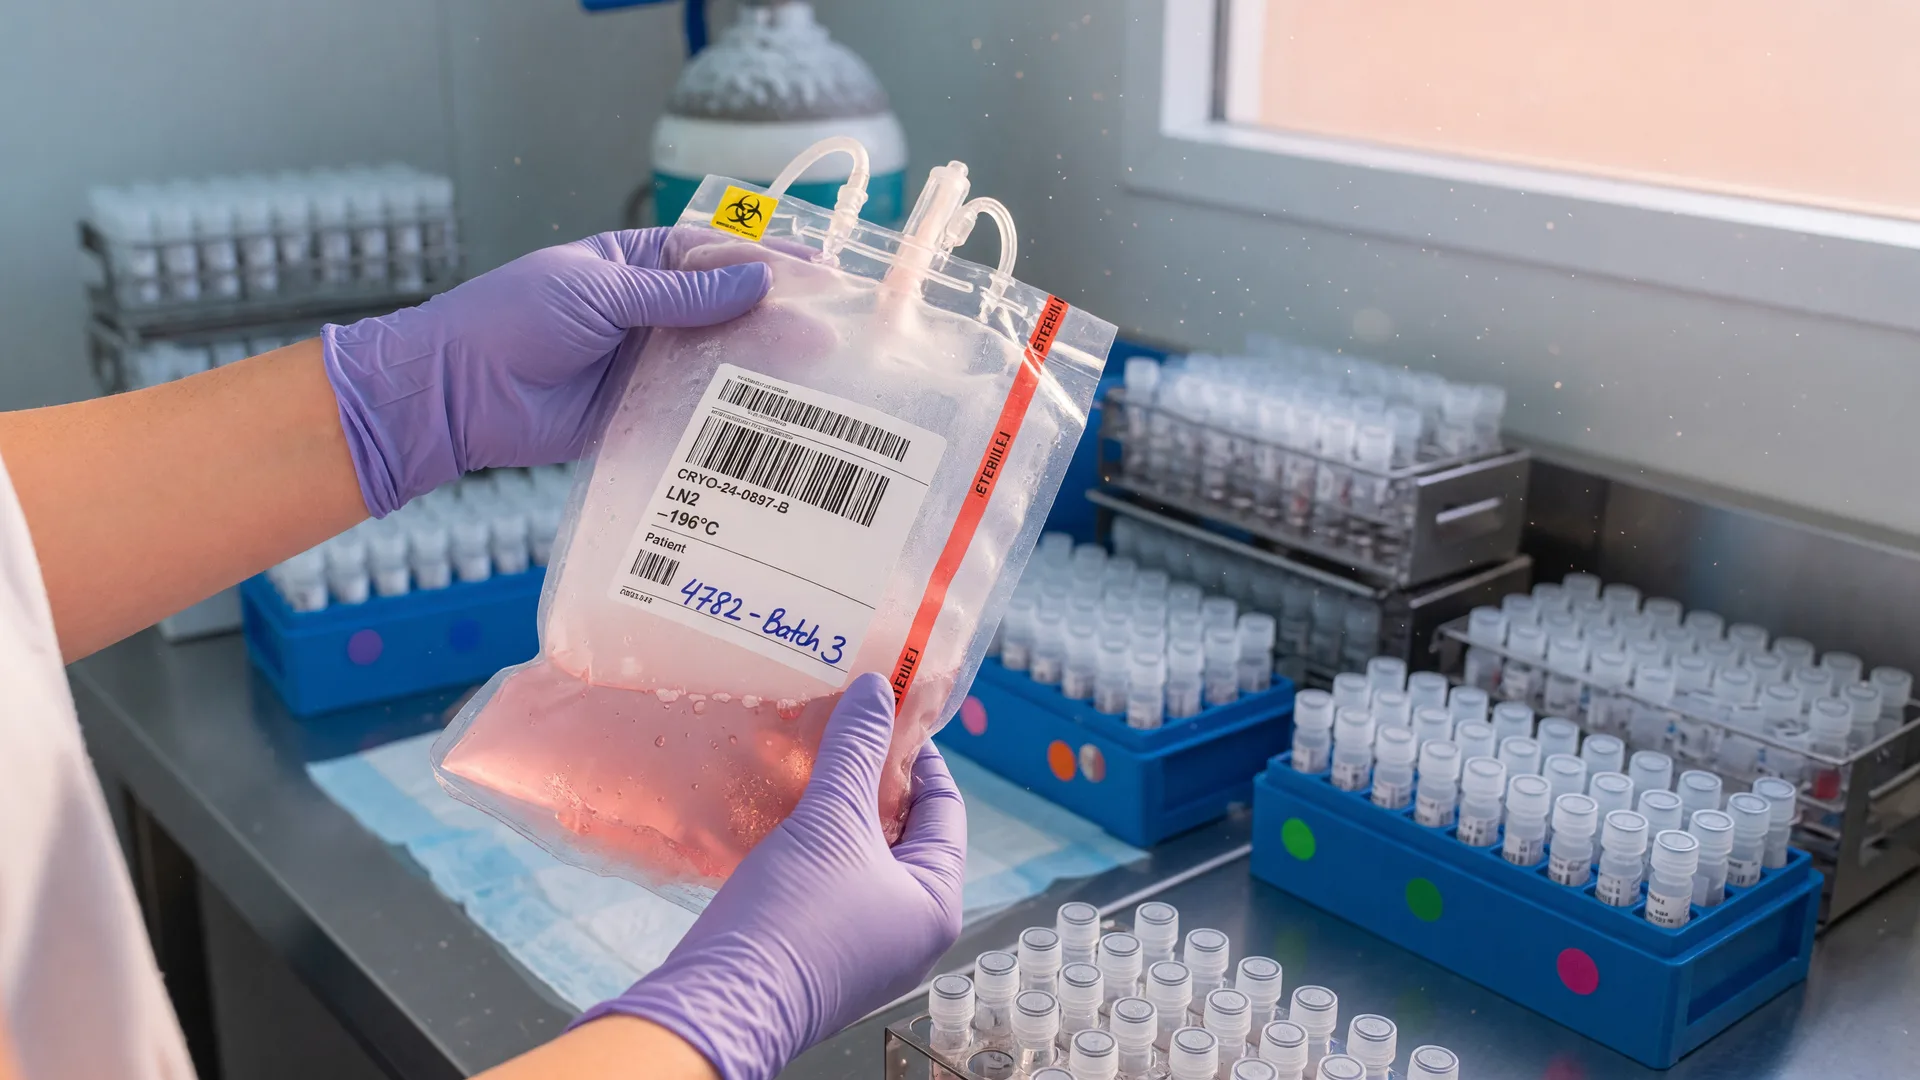
An autologous stem cell transplant starts by collecting the patient's own blood-forming stem cells, then uses high-intensity chemotherapy to deplete the immune cells that are attacking the body, and finally infuses the collected cells back so the immune system can rebuild. It is a serious procedure with real risks, performed in specialized centers, and it is not the same thing as an outpatient injection of cells into a joint. Keeping those two very different therapies in separate mental boxes matters when you evaluate claims.
Multiple sclerosis: the established use
AHSCT is now a guideline-supported option for selected people with relapsing forms of multiple sclerosis. In January 2025, the European Committee for Treatment and Research in Multiple Sclerosis (ECTRIMS) and the European Society for Blood and Marrow Transplantation (EBMT) issued joint recommendations endorsing AHSCT for the right patients. Analyses published in 2025 find higher rates of no evidence of disease activity than standard disease-modifying therapies, and long-term single-center data published in 2025-2026 show stable or improved disability scores over a median follow-up around eight years.
“In January 2025, ECTRIMS and the EBMT published joint recommendations endorsing autologous hematopoietic stem cell transplantation as an option for selected patients with multiple sclerosis.”
The randomized comparison still running
The BEAT-MS trial, sponsored by the NIH, compares AHSCT head-to-head with the best available drug therapy for treatment-resistant relapsing MS, and its results will add the strongest apples-to-apples data yet. Until it publishes, the leading randomized evidence remains an older trial that showed AHSCT clearly reduced new MRI lesions and relapse activity compared with a drug called mitoxantrone, though it did not show a significant difference in disability progression.
Lupus: promising but still experimental
The picture for systemic lupus erythematosus is different. AHSCT has been performed for severe, treatment-resistant lupus for years, and long-term cohort data show many patients achieve sustained remission, but these are single-center cohorts rather than large randomized trials. The strongest randomized transplant evidence in any autoimmune disease is actually in systemic sclerosis, where three trials showed a survival benefit over standard chemotherapy. For lupus, the EBMT published best-practice recommendations for transplant in rheumatic diseases in 2025, and a 2025 meta-analysis of randomized controlled trials of mesenchymal stromal cells found reduced disease activity without an increase in adverse events. That evidence is real and still early.
What this means for a patient in Honolulu
If you have MS or lupus, transplant questions belong in a conversation with your neurologist or rheumatologist, usually at a specialized transplant center. They are not something a local wellness clinic should market to you. The honest summary: for selected MS patients, AHSCT is an established option with real evidence; for lupus, it is a promising rescue therapy in experienced centers, and cell-based approaches remain experimental. A trustworthy stem cell page will make it immediately clear which of those categories it is actually describing.
Questions to ask before any stem cell claim targets an immune condition
Is the therapy being described a full transplant with conditioning chemotherapy, or an injection?
Does the cited evidence come from randomized trials or guidelines, or only from case reports?
Is the treating provider part of a recognized transplant or specialty center?
What are the risks of the conditioning regimen, including infection risk and effects on fertility?
Would my neurologist or rheumatologist be involved in this decision?
The bottom line
Cellular therapy has crossed into mainstream medicine in autoimmune disease, but narrowly and carefully. AHSCT for MS is the clearest success story, and lupus remains a harder case. Wherever the evidence lands, the takeaway is consistent: the best cell therapy conversations start with your own specialist, and the most dangerous ones start with a page promising the same effect from an unproven injection.
A note from the clinic
Aloha Stem Cell specializes in autologous regenerative care for joints, tendons, and soft tissue, and we do not treat autoimmune diseases with off-label infusions or injections. If you are weighing transplant options for MS or lupus, please work with your neurologist or rheumatologist. If you have questions about how regenerative medicine does and does not apply to immune conditions, our team will answer them straight. Call (808) 593-2525 or book a consultation.
Our team is happy to listen to your story, answer your questions, and help you decide
whether a consultation makes sense. There is no pressure and no obligation.
The FDA now lists Regenecyte, a cord blood stem cell product, among approved cellular therapies. It is a real milestone for blood stem cell transplant patients, and it is not a treatment for joint pain. Here is what the approval is, what it is not, and why it matters when you read stem cell news.
In September 2026 the FDA granted Fast Track status to an experimental cell therapy for ALS, and in August researchers presented new Phase 1/2 data on a stem cell therapy for Parkinson's. Both are real advances and both remain investigational. Here is the honest read.
A stem cell-derived islet therapy restored insulin production in early trials, with 10 of 12 patients insulin-independent at one year. Here is what the 2025-2026 results show, what the FDA has and has not done, and what it means for people with diabetes.