Stem Cell Therapy vs. Knee Replacement: What the 2026 Evidence Does and Does Not Show
PWritten by: Phil KimMedically reviewed by: Dr. Robert Aki, DPMLast medically reviewed: September 22, 2026
For a person with arthritic knee pain in Honolulu, the question often comes down to this: can a stem cell injection help me avoid knee replacement? It is a fair question, and the newest research gives an honest and somewhat surprising answer. A 2026 umbrella analysis found that no high-quality trial has ever directly compared stem cell injections with knee replacement surgery. This article explains what the 2025 and 2026 evidence actually shows, where the gaps are, and how to use that information in your own decision.
0
direct trials comparing stem cell injections with knee replacement, per a 2026 umbrella analysis
20-40
VAS pain-point improvement range for stem cell therapy in the trials synthesized
5.3 yr
median delay of knee replacement in a large PRP retrospective cohort
The question patients actually ask
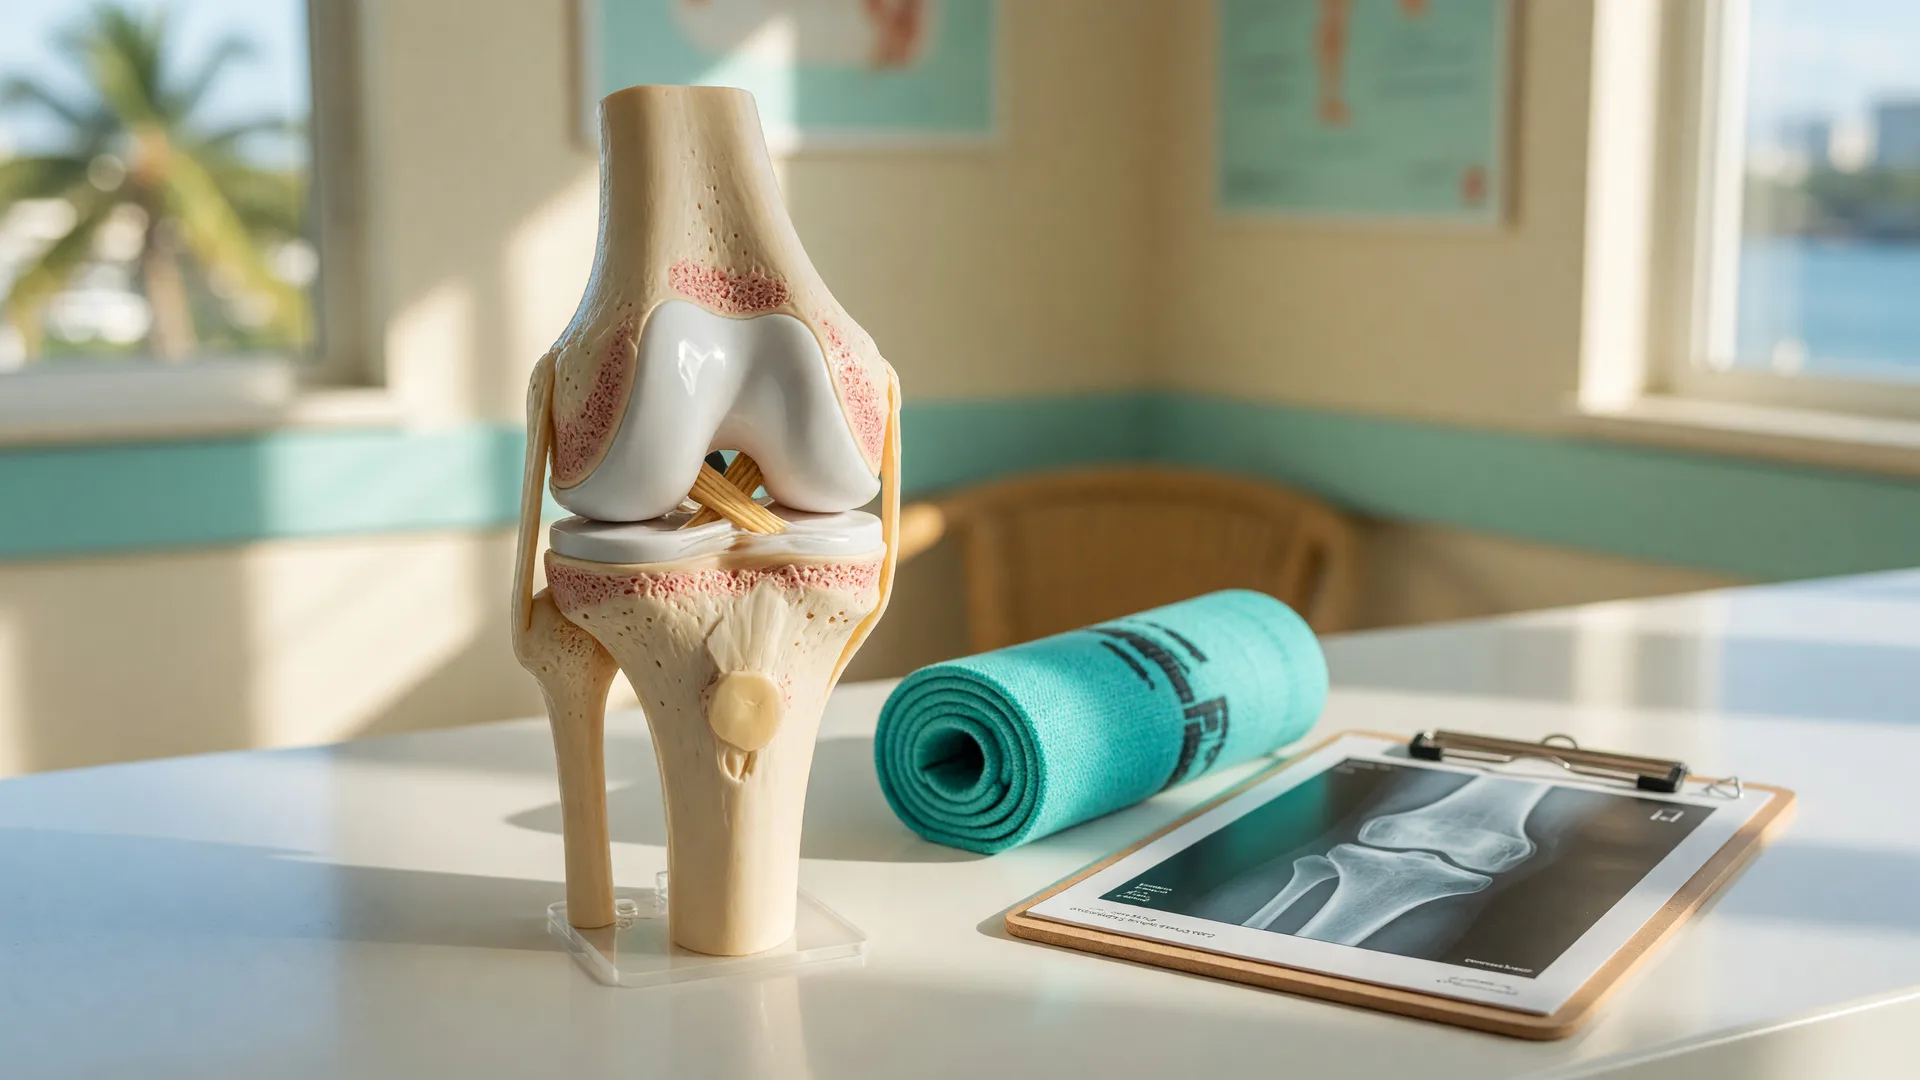
Knee osteoarthritis is one of the most common reasons people explore regenerative medicine, and knee replacement is the standard answer for advanced, bone-on-bone disease. In between sits a large group of people with moderate arthritis who are not ready for surgery, and who ask whether an injection could delay or avoid it. That question is reasonable, but comparing a 30-minute injection with a major operation requires evidence that directly pits the two against each other. Turns out, that evidence barely exists.
The 2026 evidence gap: no direct head-to-head trials
A 2026 umbrella analysis titled Total Knee Arthroplasty versus Mesenchymal Stem Cell Therapy for Moderate Knee Osteoarthritis reviewed the entire landscape of trials on this exact question. Its most important finding was a profound gap: zero studies have directly randomized or compared stem cell injection against knee replacement. Instead, the analysis synthesized 30 high-quality trials that compared stem cell therapy with placebo or conservative care, finding meaningful improvements in pain and function, with VAS pain reductions in the range of 20 to 40 points and gains on the WOMAC scale, and it concluded stem cell therapy may serve as an alternative or bridge for people with moderate, KL grade 2 to 3 arthritis. It is a hopeful but indirect answer, and the authors were explicit that direct comparison data simply do not exist yet.
“A 2026 umbrella analysis found zero studies directly comparing stem cell injection with knee replacement, while synthesizing 30 high-quality trials in which stem cell therapy meaningfully outperformed placebo and conservative care for moderate knee osteoarthritis.”
A 2025 caution: how much is the placebo effect?
The other side of the coin came in a 2025 systematic review and meta-analysis in Frontiers in Medicine, which examined the contextual effects of stem cell injections for knee osteoarthritis. It concluded that a large share of the symptomatic improvement seen in these trials is attributable to contextual or placebo effects, with only a modest incremental benefit coming from the cells themselves, and judged the evidence low-certainty. Read together with the umbrella analysis, the fair summary is this: injections appear to help many people with moderate arthritis, but exactly how much of that help comes from the biology versus the context of care is still being sorted out. That is precisely why honest clinics avoid promising a specific result.
What the data show about delaying surgery
The best evidence on delaying knee replacement comes not from randomized trials but from long-term observational studies. One well-known retrospective analysis of over 200 patients found that PRP injections delayed the need for knee replacement by a median of about 5.3 years, with roughly 86 percent of patients avoiding surgery at five years. A randomized 15-year follow-up of bone marrow concentrate similarly reported that the treatment helped many patients postpone total knee arthroplasty. These are encouraging outcomes, but they come from fewer, less controlled studies, and they describe an average, not a guarantee. For advanced bone-on-bone disease, joint replacement remains the standard of care, and no injection should be sold as its replacement.
“A large retrospective study found PRP injections delayed the need for knee replacement by a median of about 5.3 years, with roughly 86% of patients avoiding surgery at five years.”
The 2026 real-world caution on PRP
A 2026 real-world cohort published in PLOS ONE tracked patients for five years and found that a single short course of leukocyte-poor PRP did not sustain clear superiority over standard conservative care over the long term. The study is a reminder that real-world results can lag behind early trial enthusiasm, and that a single injection is not a substitute for a treatment plan that includes strength, activity management, and follow-through over years.
What this means for a Honolulu patient
If you are weighing regenerative treatment against knee replacement, the honest framework looks like this: for mild to moderate arthritis, an injection may reduce pain, support function, and help you stay active while you strengthen the joint, and it may delay surgery in some people, on average, for years. For advanced bone-on-bone disease, surgery is typically the more honest path, and a trustworthy clinic will say so plainly. Either way, the decision should start with imaging that grades your arthritis, a conversation about the strength of the evidence for your specific knee, and a plan that treats injections as a bridge, not a magic switch.
Questions to ask
What grade is my knee arthritis on imaging, and what is driving my pain?
Have I done structured strengthening and weight management first?
Is the evidence for injections in my specific situation strong, mixed, or still early?
Is the person recommending treatment a surgeon or a clinic with no surgical option?
If injections delay but do not eliminate the need for surgery, what does that timeline look like honestly?
A note from the clinic
Knee replacement is a life-changing decision, and so is choosing to try an injection first, and neither deserves hype. At Aloha Stem Cell in Honolulu we will review your imaging, explain what the newest evidence does and does not support, and tell you honestly whether regenerative treatment is a reasonable bridge for your knee, or whether surgery is the more honest path. Call (808) 593-2525 to talk it through.
Our team is happy to listen to your story, answer your questions, and help you decide
whether a consultation makes sense. There is no pressure and no obligation.
The FDA now lists Regenecyte, a cord blood stem cell product, among approved cellular therapies. It is a real milestone for blood stem cell transplant patients, and it is not a treatment for joint pain. Here is what the approval is, what it is not, and why it matters when you read stem cell news.
In September 2026 the FDA granted Fast Track status to an experimental cell therapy for ALS, and in August researchers presented new Phase 1/2 data on a stem cell therapy for Parkinson's. Both are real advances and both remain investigational. Here is the honest read.
A stem cell-derived islet therapy restored insulin production in early trials, with 10 of 12 patients insulin-independent at one year. Here is what the 2025-2026 results show, what the FDA has and has not done, and what it means for people with diabetes.